
Choosing the best Reusable OR Grade Surgical Instruments means looking beyond price and appearance. A clamp must close smoothly, a scissors’ edges must meet cleanly, and a handle must remain comfortable through repeated use. Yet these details matter only when the instrument also suits its intended procedure and can withstand its validated cleaning and sterilization processes. Small flaws can be easy to miss.
The stakes extend beyond the instrument tray. The World Health Organization’s Global Report on Infection Prevention and Control (2022) estimates that 7 in 100 hospitalized patients in high-income countries, and 15 in 100 in low- and middle-income countries, acquire at least one healthcare-associated infection. These figures do not attribute infections to surgical instruments, but they underline why dependable reprocessing deserves close attention. Dr. William A. Rutala, an infection-prevention expert, has put it plainly: “Cleaning is the most important step in the reprocessing of reusable medical devices.” His point is practical. A premium instrument cannot compensate for an inadequate cleaning process.
This guide compares instruments by material quality, precision, ergonomics, repairability, and compatibility with facility reprocessing protocols. It also considers manufacturer documentation and service support, not just catalog claims. No single instrument is best for every operating room. The right choice depends on the procedure, staff feedback, and the demands of repeated use. We should acknowledge one limitation: published head-to-head performance data can be sparse, so careful evaluation matters.
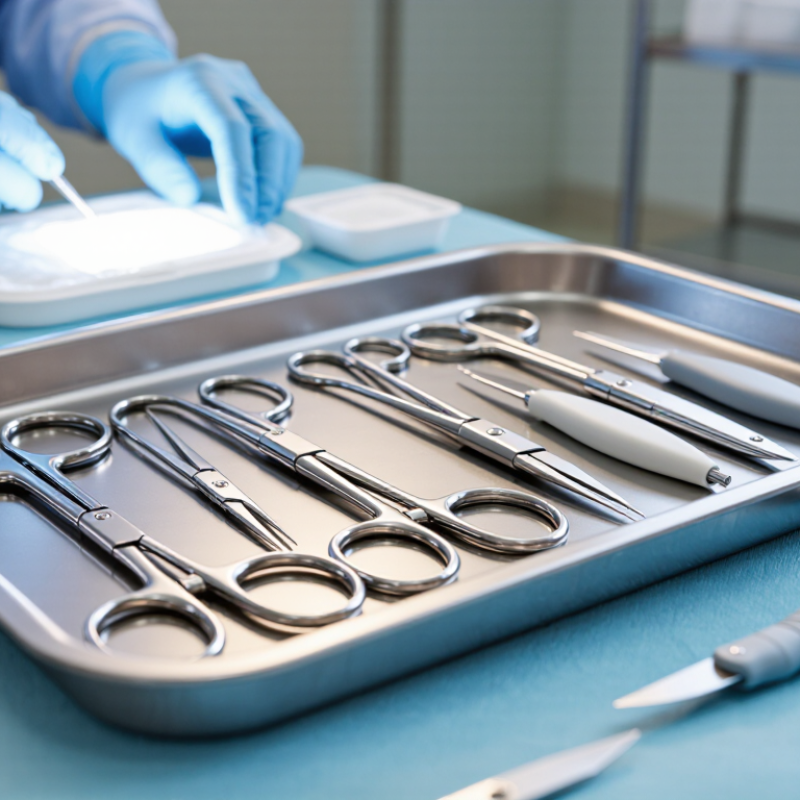
“OR-grade reusable surgical instruments” is a practical description, not a standalone ISO classification. It generally refers to instruments designed for repeated clinical use, with materials, joints, and finishes able to tolerate specified reprocessing cycles. The label alone proves little. A stainless-steel clamp may look robust, yet a tight hinge can trap soil after use. That distinction matters. Reliable performance depends on function, durability, and clear processing instructions, not appearance alone.
ISO 17664-1:2021 sets requirements for processing information supplied by manufacturers for critical and semi-critical medical devices. It is not a certification of an instrument’s quality. Instructions should address applicable steps such as point-of-use preparation, cleaning, rinsing, drying, inspection, maintenance, packaging, sterilization, and storage. They should specify equipment, conditions, and cycle parameters clearly enough for trained staff to follow. Small details count. For example, instructions should explain whether a hinged instrument must be opened during cleaning and how damage or residual soil should be checked. Real workflows are messy; even sound instructions can be difficult to follow at a crowded sink. Staff should use the device-specific instructions and report unclear steps. OR-grade selection should consider both the instrument’s clinical function and whether its reprocessing guidance is complete, validated, and practical.
OR-grade describes instruments intended for operating-room use; it is not a formal ISO quality grade. Reusable instruments should be selected for their intended procedure and for compatibility with validated reprocessing instructions.
How to read this chart: Each bar represents a processing-information topic—not a score or a measure of instrument quality. The applicable steps and parameters depend on the device and its manufacturer’s instructions for use (IFU).
ISO 17664-1:2021 addresses information manufacturers provide for processing critical and semi-critical medical devices. It does not certify an instrument or prescribe one universal reprocessing cycle. Check that the IFU provides applicable instructions and that the instrument can tolerate the specified cleaning, disinfection, and sterilization processes.
What Are the Best Reusable OR Grade Surgical Instruments?
ASTM F899 helps compare stainless steels used in surgical instruments by material class and grade. It does not make every instrument equally suitable for every task. Martensitic grades, including common 420 and 440 variants, can be heat-treated for hardness and edge retention. They are often considered for cutting instruments, but their corrosion resistance depends on grade, finish, and care. Small staining around a joint is a warning, not just a cosmetic flaw.
Austenitic grades, such as 304 and 316, generally offer strong corrosion resistance but cannot be hardened like martensitic steels. They may suit instrument designs where toughness and resistance to repeated processing matter more than a keen cutting edge. Precipitation-hardening stainless steels gain strength through controlled heat treatment, offering another balance of strength and corrosion performance. Details matter. Check the specified F899 grade, not only the broad class, and confirm that the instrument’s intended use matches its properties. After processing, inspect serrations, box locks, and narrow hinges under good light. A material class is a useful starting point, but it cannot replace validated cleaning, sterilization, and maintenance practices. Even careful teams can miss wear. That deserves honest review.
The best reusable OR-grade surgical instruments are not defined by appearance alone. Their durability should be judged after repeated cleaning and sterilization, not just during a first inspection. Examine hinges, serrations, and box locks for staining, looseness, or rough movement. A hemostat should open smoothly and hold its grip without excessive pressure. Small flaws matter.
Ergonomics show up during real tasks. Check whether handles sit comfortably in a gloved hand, whether finger rings allow controlled movement, and whether instruments are easy to identify on a tray. Then review the manufacturer’s validated reuse instructions and cycle limits for the specific instrument. A validated cycle is not a promise of unlimited service life. Staff should document use, follow the stated cleaning and sterilization parameters, and inspect instruments before each procedure. Not always easy.
Workflow can complicate ideal maintenance. Busy teams may miss subtle wear, so practical inspection criteria and staff training matter. Replace or remove an instrument from service when its function, surface, or alignment raises concern. The paperwork can feel tedious, but it helps connect observed condition with approved reuse limits. A durable instrument still needs careful handling, consistent processing, and honest reassessment.
The best choice depends on the procedure, instrument design, and the facility’s reprocessing workflow. This comparison describes common reusable instrument categories; it does not rank specific products.
| Instrument category | Durability considerations | Ergonomics to assess | Reuse-cycle validation | Routine inspection points |
|---|---|---|---|---|
| General-purpose forceps | Reusable forceps are commonly made from corrosion-resistant stainless steel. Serviceability depends on construction, handling, cleaning, and reprocessing. | Assess grip comfort, balance, spring action, and whether the jaw pattern provides suitable control for the intended task. | Follow the exact instrument’s instructions for use (IFU). There is no universal validated cycle limit for this category. | Check jaw alignment, tips, surface condition, and smooth opening and closing; remove damaged instruments from service. |
| Surgical scissors | Cutting performance can decline with wear or damage. Material, edge design, and any manufacturer-defined servicing requirements vary by instrument. | Consider handle fit, finger-ring comfort, balance, and smooth movement through the working range. | Use the model-specific IFU for reprocessing and any stated reuse limit; do not infer a cycle count from the instrument category. | Inspect cutting edges, tip condition, joint movement, and alignment. Verify cutting function using the facility’s approved inspection process. |
| Needle holders | Some designs use hardened jaws or carbide inserts; features are not universal. Joints, ratchets, and jaw surfaces require appropriate cleaning and inspection. | Assess handle comfort, ratchet release, grip security, and control when holding the needle. | The permitted reuse or processing limit, if specified, is instrument-specific and must come from the applicable IFU. | Check jaw alignment and grip, ratchet function, joint condition, and any inserts for looseness or damage. |
| Retractors | Reusable retractors may be fixed or self-retaining. Hinges, joints, and locking mechanisms add inspection and cleaning considerations. | Evaluate handle access, adjustment, locking action, and suitability for the procedure and surgical team. | A category-wide validated cycle count is not available. Follow the specific device IFU and facility reprocessing procedures. | Inspect joints, teeth or blades, locking function, and surfaces for damage or corrosion; confirm moving parts function correctly. |
| Reusable laparoscopic instruments | May include shafts, joints, insulation, seals, or detachable components. Construction and reprocessing requirements differ across designs. | Assess handle comfort, actuation force, rotation, balance, and control through the intended range of motion. | Use only the applicable IFU for validated reprocessing instructions and any stated cycle limit. No general cycle number applies to all designs. | Inspect insulation, shaft, jaws, seals, connections, and moving parts as directed by the IFU; use required insulation testing where specified. |
Important: Reprocessing-cycle limits are device-specific and may not be stated as a single numerical maximum. A sterilization cycle is not necessarily the same as a clinical-use count. Follow the current IFU for the exact instrument, including cleaning, inspection, sterilization, maintenance, and retirement criteria.
Reusable OR-grade instruments depend on validated reprocessing, not appearance. AAMI ST79 guidance treats cleaning, inspection, packaging, sterilization, and documentation as connected controls. Soil trapped in a box lock can shield microbes from steam. A clean-looking hinge is not proof.
The CDC’s Guideline for Disinfection and Sterilization in Healthcare Facilities recommends biological indicator testing at least weekly and for every load containing implants. It also advises quarantining implant loads until results are negative, when feasible.
A 10⁻⁶ sterility assurance level (SAL) means a theoretical probability of no more than one viable microorganism per million sterilized items. It is a process-validation benchmark, not a test result for each instrument.
Steam cycle settings vary by load and device; CDC guidance lists examples such as 132°C for four minutes in a prevacuum cycle. Follow validated instructions and AAMI ST79 requirements, rather than copying a cycle by habit.
Small workflow gaps matter. A missed lumen brush or wet pack deserves review, even when the indicator passes. The data can feel reassuring, but it cannot replace careful inspection and complete records.
The best reusable instruments depend on the procedure, the team’s handling preferences, and the facility’s reprocessing capacity. For delicate dissection, fine, balanced forceps can help with controlled tissue handling; heavier clamps suit tasks that require a firmer grip. A laparoscopic case may call for long-shaft instruments with smooth, reliable articulation. Open procedures often benefit from familiar hand-feel and clear visibility of the working end.
Small differences matter. A handle that fits one clinician’s grip may tire another’s hand during a long case.
Maintenance needs should shape the choice, too. Hinges, ratchets, insulated sections, and narrow channels can require close inspection and careful cleaning. Teams should follow the instrument’s instructions for use and their validated cleaning and sterilization processes. Look for corrosion, loose joints, damaged insulation, or dull cutting edges before instruments return to service.
A common mistake is choosing a large set for flexibility, then overlooking the extra inspection and storage it demands. More instruments are not always better.
Even a carefully selected set may need adjustment after staff use it; feedback about grip, balance, and cleaning difficulty can reveal practical issues that specifications miss.
It describes an instrument designed for repeated clinical use. The label alone does not prove quality or durability.
It covers processing instructions for critical and semi-critical devices. These may include cleaning, rinsing, drying, inspection, sterilization, and storage.
No. It addresses the processing information supplied with a device, not its overall quality.
Check the specified ASTM F899 grade, not just the steel class. Match its properties to the instrument’s intended use.
Look closely at hinges, serrations, and box locks. Staining, looseness, or rough movement may signal a problem.
Test the handles with gloved hands. Finger rings should allow controlled movement, and the instrument should be easy to identify on a tray.
No. Follow the stated cycle limits and processing instructions. Inspect each instrument before use.
Remove it if its function, surface, or alignment raises concern. Subtle wear can be easy to miss.
Clear steps help staff clean complex areas, such as a tight hinge. Crowded workflows can still make careful processing difficult.
Reusable OR Grade Surgical Instruments are designed for repeated clinical use while maintaining function, safety, and reliable performance. Their suitability depends on more than appearance: materials should be assessed against the relevant ASTM F899 class, while design, corrosion resistance, joint construction, and ergonomic handling all affect performance. Selection should also account for the intended procedure, the demands placed on each instrument, and a practical plan for inspection, maintenance, and replacement.
Safe reuse relies on validated processing as well as durable construction. Manufacturers’ instructions for use should specify cleaning, disinfection, inspection, packaging, sterilization, and any limits on reuse in accordance with ISO 17664-1:2021. Reprocessing programs should follow applicable AAMI ST79 guidance and demonstrate the required sterility assurance level, commonly expressed as a 10⁻⁶ SAL benchmark. Together, material evaluation, validated reuse information, careful handling, and consistent reprocessing help facilities choose instruments that meet procedural needs and support dependable care.
