
0%

Choosing Custom Surgical Instrument Sets in 2026 requires more than selecting attractive finishes or adding familiar tools. Hospitals must connect each set with actual procedures, surgeon preferences, sterilization capacity, and patient safety goals. A tray that looks complete may still contain the wrong clamp, an unnecessary retractor, or too many repeated instruments. That creates weight, confusion, and processing delays.

Dr. Atul Gawande, a surgeon and patient-safety authority, wrote, “The volume and complexity of what we know has exceeded our individual ability to properly deliver its benefits.” His observation remains highly relevant to Custom Surgical Instrument Sets. Modern procedures demand precision, yet complexity can quietly increase handling errors. The right set should support a clear surgical workflow, not display every possible instrument.

A practical evaluation begins with procedure mapping. Review operative steps, surgeon feedback, instrument frequency, and sterilization records. Measure tray weight and check whether staff can identify each instrument quickly. Examine hinges, box locks, insulation, markings, and corrosion resistance under repeated use. Small details matter.

Ask hard questions.

Does the set reduce unnecessary opening?

Can nurses recognize missing instruments immediately?

Will the configuration remain useful after technique changes?

There is no perfect tray. That deserves honesty. A custom design may improve efficiency, but it can also create dependence on one surgeon’s habits. Preferences change. Inventory mistakes happen. Therefore, hospitals should test the set in supervised cases, collect feedback, and revise it before full adoption. In 2026, the strongest choice will balance clinical familiarity, measurable performance, lifecycle cost, and reliable reprocessing.
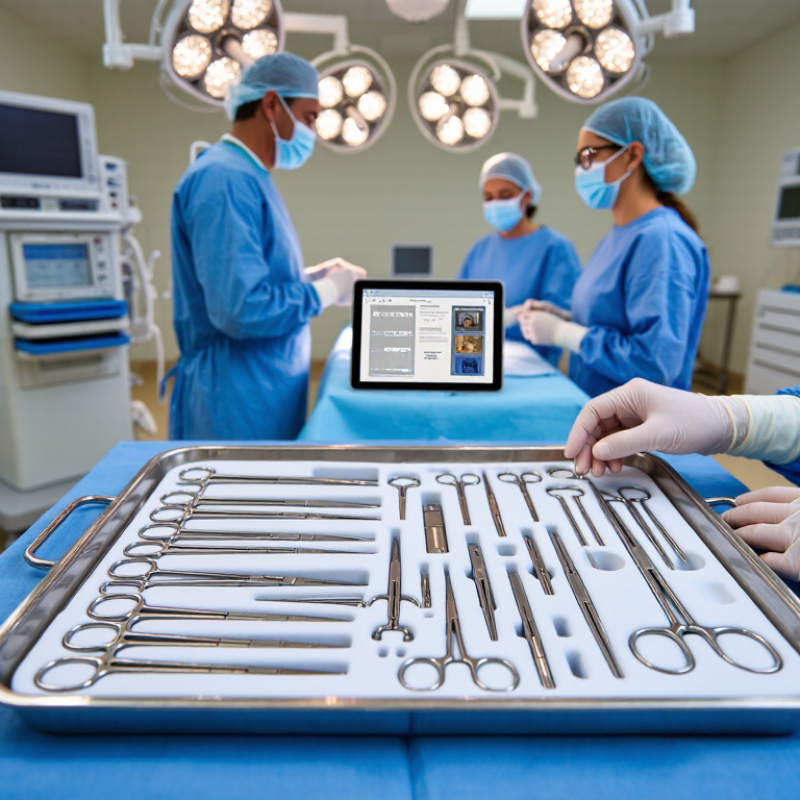
How to Choose Custom Surgical Instrument Sets in 2026?

Map Procedures, Volumes, and Instrument Needs Before Customization

Custom surgical instrument sets should begin with procedure mapping, not a catalog. List each operation, its critical steps, and the instruments required for every step. Then separate essential, backup, and rarely used items. Volume changes everything. A low-volume procedure may justify a flexible shared set, while high-volume cases need dedicated trays to reduce turnover delays. The Lancet Commission on Global Surgery estimated 313 million operations occur globally each year, showing why local demand data matters (Lancet Commission on Global Surgery, 2015).

Review at least 12 months of case records, including cancellations, emergencies, seasonal peaks, and surgeon preferences. Calculate average weekly volume and identify instruments repeatedly opened but rarely used. That gap matters. It increases handling, inspection, sterilization, and storage demands. The World Health Organization recommends standardized surgical safety processes, including instrument accountability during procedures (WHO, WHO Guidelines for Safe Surgery 2009). Your set design should support those checks without creating unnecessary complexity.

A practical worksheet can connect procedure names, monthly volume, tray capacity, sterilization cycles, and replacement needs. Confirm cleaning instructions and material compatibility against current reprocessing requirements, including AAMI ST79 guidance for steam sterilization. Do not assume one “universal” set fits every facility. Staffing, room size, emergency coverage, and local sterilization capacity can change the answer. The map is never perfect. Pilot the configuration, measure missing instruments and unused items, then revise it after real cases. A first draft may still be wrong. That is useful information.

Set Sterility Targets at SAL 10⁻⁶ Under ISO 11135 and ISO 11137

Choosing a custom surgical instrument set in 2026 requires more than matching instruments to procedures.

Sterility targets must be defined early, with a Sterility Assurance Level (SAL) of 10⁻⁶ commonly used for terminal sterilization. This represents a one-in-a-million probability of a viable microorganism surviving the validated process. It is a probability, not a test result.

ISO 11135 guides ethylene oxide sterilization, while ISO 11137 covers radiation sterilization. The correct pathway depends on material compatibility, packaging, device geometry, and production volume.

Hinges, narrow channels, dense metal trays, and nested instruments can challenge sterilant or radiation uniformity. Small details matter.

Validation should examine bioburden, load patterns, packaging integrity, and worst-case configurations. Biological indicators support EO studies, while dose mapping and dose audits support radiation processes.

EO systems also require attention to residual limits and aeration time. A clean-looking set is not necessarily sterile.

In practice, the selected set should be tested as it will actually be assembled. Not as an ideal laboratory model.

I have found that overfilled trays create avoidable uncertainty. That assumption deserves review.

Routine monitoring, documented release criteria, and periodic requalification help maintain control under ISO 11135 or ISO 11137. Local regulatory requirements may add further expectations.

Meet ISO 13485, FDA QMSR, and EU MDR Documentation Requirements

How to Choose Custom Surgical Instrument Sets in 2026?

Choosing a custom surgical instrument set now requires more than reviewing dimensions and pricing. The supplier should show an ISO 13485-based quality system, controlled design records, and documented risk management. Under the FDA QMSR, quality procedures must align with applicable medical device requirements. Ask how design changes, supplier evaluations, nonconformities, and complaint investigations are recorded.

Request a complete documentation map before approving prototypes. It should connect user needs to specifications, drawings, verification tests, and validation evidence. For EU MDR readiness, review the technical documentation, intended purpose, classification rationale, labeling, traceability, and post-market surveillance plan. Sterilization instructions need supporting validation, not attractive wording. Material certificates and biocompatibility assessments should match the final instrument configuration.

Details matter.

In practical reviews, small gaps often create larger delays. A missing revision number can disconnect a test report from the approved drawing. An outdated cleaning instruction can weaken the device file. Ask for sample records, not general promises. Check whether each instrument has a clear identifier and whether set-level changes trigger documented review. No checklist is perfect. Teams can still overlook an accessory or assume a familiar material needs no reassessment. That is where careful questioning helps. Select a partner that explains evidence clearly, admits limitations, and maintains controlled records through production, delivery, and future changes.

Engineer Trays Around AAMI ST79’s 25-Pound Set-Weight Guidance

How to Choose Custom Surgical Instrument Sets in 2026?

Custom trays should begin with weight, not convenience. ANSI/AAMI ST79 recommends keeping a sterilization set at or below 25 pounds, including instruments and the container. This limit supports steam penetration, drying, safe handling, and consistent sterilizer performance. A heavier tray may look efficient, but it can hide wet surfaces, crowded hinges, and uneven instrument exposure. Those details matter. The CDC’s national point-prevalence survey found that about one in 31 U.S. hospital patients had a healthcare-associated infection. Tray design cannot prevent every infection, but reliable processing reduces avoidable risk.

Measure real case demand before selecting instruments. Review procedure logs, missing-item reports, repair records, and sterilization failures. Place dense retractors near the base, then separate delicate items with protective supports. Use a small number of clearly labeled modules instead of one overloaded container. In practice, teams often discover unused instruments after observing several procedures. That finding deserves attention. More instruments do not always create better readiness. A lightweight tray can also improve staff handling, but the 25-pound target should not replace local validation, manufacturer instructions, or sterilizer testing.

Tips: Weigh the complete loaded tray. Record the result. Test drying after a full cycle. Ask sterile-processing staff to inspect the tray layout. Recheck the design after three months. Human assumptions can be wrong.

How to Choose Custom Surgical Instrument Sets in 2026?

Engineer trays around AAMI ST79’s 25-pound set-weight guidance

The chart converts common tray-weight reference points from pounds to kilograms using 1 lb = 0.45359237 kg. The highlighted line marks 25 lb, equivalent to approximately 11.34 kg. Treat this value as an engineering and handling reference, then confirm the current AAMI ST79 edition, sterilizer limits, packaging requirements, and facility policy before finalizing a custom set.

Validate Prototypes Through OR KPIs, Reprocessing Cycles, and Cost Data

Selecting custom surgical instrument sets in 2026 should begin with evidence from real operating rooms. A prototype may look efficient on a design table. That proves little. Test it during representative procedures, with surgeons, nurses, and sterile processing staff involved. Record setup time, instrument retrieval time, count discrepancies, tray weight, and interruptions caused by missing tools. Keep the same procedure types and staffing levels when comparing designs. Small details matter. A heavy tray can strain staff before the incision begins.

Use clear OR KPIs across several cases, not one successful trial. Measure procedure duration, unplanned instrument opening, handling errors, and surgeon-requested substitutions. In one pilot, a textured handle seemed secure with dry gloves but slipped with moisture. The design required revision. The first dataset was also too small. That weakness should be documented, not hidden.

Reprocessing validation needs repeated cycles under approved cleaning and sterilization instructions. Inspect joints, insulation, markings, hinges, and cutting edges after each cycle. Track damage, retained soil, drying problems, and packaging failures. A set that performs well in surgery may still create processing delays. Cost analysis should include purchase price, staff minutes, repairs, replacement instruments, storage space, and OR delays. Use actual invoices and time logs where possible. Estimates can mislead. Review the data with quality, clinical, and sterile processing leaders before approving the final configuration.

How to Choose Custom Surgical Instrument Sets in 2026? - Validate Prototypes Through OR KPIs, Reprocessing Cycles, and Cost Data

An anonymized prototype-validation scorecard using measurable operating-room, reprocessing, quality, and lifecycle-cost indicators

Prototype Configuration OR Performance KPIs Reprocessing and Quality Cost and Decision
Prototype Instrument Count Tray Weight Setup Time Missing-Item Events Instrument Exchange Time Staff Usability Score Completed Reprocessing Cycles Cleaning Failures Functional Failures Packaging Damage Events Acquisition Cost / Set Annual Reprocessing Cost / Set Validation Result
A — Standard Core 42 8.6 kg 6.8 min 3 / 120 cases 24 sec 4.1 / 5 100 2 / 100 1 / 100 1 / 100 $12,800 $3,420 Conditional
B — Lean Modular 34 6.9 kg 5.1 min 1 / 120 cases 18 sec 4.6 / 5 100 0 / 100 0 / 100 0 / 100 $11,950 $2,760 Preferred
C — Expanded Specialty 58 11.7 kg 9.4 min 5 / 120 cases 31 sec 3.7 / 5 100 6 / 100 3 / 100 2 / 100 $15,600 $4,680 Reject / Redesign
Recommended acceptance gates
Setup time ≤ 6 minutes; missing-item events ≤ 2 per 120 cases; usability score ≥ 4.3 / 5.
Reprocessing evidence
Complete cleaning, inspection, functional checks, packaging inspection, and traceable cycle records before approval.
Cost interpretation
Annual reprocessing cost includes labor, water, detergent, energy, inspection, packaging, and routine maintenance assumptions.

Measurement basis: 120 observed procedures per prototype, 100 documented reprocessing cycles per prototype, and a 12-month operating-cost model. Thresholds should be confirmed through the facility’s quality system, validated manufacturer instructions, and applicable requirements such as ISO 17664-1, ISO 11607, and AAMI ST79. Currency is shown in USD; cost figures exclude taxes, capital depreciation, and transportation.

FAQS

What should guide the design of a custom surgical instrument set?

Begin with each procedure, its critical steps, and the instruments needed for every step. Separate essential, backup, and rarely used items. Catalogs should not lead the decision.

How much case data should a facility review?

Review at least 12 months of records, including cancellations, emergencies, seasonal peaks, and surgeon preferences. Calculate average weekly volume. Patterns can be surprising.

How does procedure volume affect tray design?

Low-volume procedures may share flexible sets. High-volume procedures usually need dedicated trays. This can reduce turnover delays and repeated searching.

Why should rarely used instruments be removed?

Rarely used instruments increase handling, inspection, sterilization, and storage demands. They also add weight and crowd the tray. More is not always better.

What weight should a sterilization tray target?

Keep the complete loaded tray near or below 25 pounds. Include the instruments and container when weighing. Measure the loaded tray.

How can a heavy tray create processing problems?

Excess weight may limit steam penetration, drying, and safe handling. Crowded hinges and wet surfaces can remain hidden. That risk deserves attention.

How should instruments be arranged inside the tray?

Place dense retractors near the base. Protect delicate instruments with suitable supports. Use several clearly labeled modules instead of one overloaded container.

What should be tested before approving a custom configuration?

Pilot the tray during real procedures. Record missing instruments, unused items, drying results, and handling concerns. Then revise the design.

Which local factors can change the best tray configuration?

Staffing, room size, emergency coverage, sterilizer capacity, and cleaning requirements all matter. One universal set rarely fits every facility. Local validation remains necessary.

How often should the tray design be reviewed?

Recheck the configuration after about three months and after major workflow changes. A first draft may be wrong. That is useful information.

Conclusion

Choosing Custom Surgical Instrument Sets in 2026 requires a structured approach that connects clinical needs with safety, compliance, and operational efficiency. Start by mapping the procedures your facility performs, expected case volumes, and the instruments required for each workflow. This helps prevent unnecessary items, reduce duplication, and create sets that support efficient operating-room performance. Sterility goals should be defined at a Sterility Assurance Level of 10⁻⁶, with processes aligned to ISO 11135 and ISO 11137 where applicable.

Documentation and quality systems must also support ISO 13485, FDA QMSR, and EU MDR expectations. Tray design should consider AAMI ST79 guidance, including the practical 25-pound set-weight recommendation, to improve handling and reduce reprocessing challenges. Before full production, validate prototypes through operating-room KPIs, repeated reprocessing cycles, usability feedback, and detailed cost analysis. A successful set is not simply complete; it should be safe, traceable, easy to process, and financially sustainable throughout its service life.

Evelyn

Evelyn

Evelyn is a professional marketing specialist with a strong understanding of the company’s products, services, and the needs of the customers they support. She regularly contributes expert articles to the company website, translating product knowledge and industry insights into clear, practical......